
Caring for the Elderly: Part 6
Once again, I find myself writing about this subject in the hope that it will encourage others to reflect upon the nature of old age, illness and the consequences that arise from them. There is still a prevailing culture of not discussing and sometimes not even thinking about such matters, but both are an absolute certainty in everyone’s life. All too often people find themselves in extremely difficult situations brought about by such events and the difficulty and emotional trauma is increased due to there being no plan in place or provision to address matters. Therefore, I strongly advocate the following. Some may seem like very obvious points, but recent conversations I’ve had with other carers and people in similar situations, has shown that many people have not made even the most basic of provisions in this regard.
Life insurance: There are a broad range of policies available and it really comes down to what you can afford and what you wish to achieve. You may wish to consider cover that pays during prolonged periods of illness or simply a policy that cover the expense of a funeral. It doesn’t have to be a complex or daunting process. Having life insurance in place affords you piece of mind that your loved ones will not be financially troubled if illness or death occur.
Last Will and Testament: Ensuring that you have a will is also a source of peace of mind. It ensures that your assets and property are smoothly transferred to those you choose and that your funeral arrangements are clear in advance. For most people it does not have to be a complex process and often a simple standard document will suffice. The absence of such a provision can lead to additional administrative and legal issues at a time when they are least needed.
Living Wills and Care Plans: I wrote in my previous post about DNR notices and again would like to highlight the importance of discussing in advance the long term wishes of the person you care for. Clear and honest communication are paramount, and it is counterproductive to shy away from such issues because it makes you feel awkward or sad. Everyone has their own unique view on what is acceptable and what is not when it comes to the quality of their own life. Therefore, it is practical to consider and plan for certain eventualities, regardless of whether they are imminent or not.
Another matter it is wise to consider in advance is the general increase in household expenditure that can occur as a result of getting old and infirm. Carers, medical supplies, house alterations and minor changes to one’s lifestyle all contribute to increased monthly spending. In the UK, there are benefits and allowances available to help with such costs, but they are often means tested. Sometimes families prefer to take control of such services themselves and make their own financial arrangements. In my father’s case, not only does he choose to employ a very specific care company to assist him twice a day, he also spends additional funds on disposable items such as batteries, kitchen towel and incontinence pants. All of which have a cost that adds to the monthly budget. Furthermore, my parent’s household produces a lot more domestic waste than the average home. They quickly found that the standard refuse bin was not adequate for their needs, so we had to apply for an additional one from the local authority.
Modern day life is very much focused on living in the moment. As a result, long term decisions are often overlooked or simply ignored. When you’re twenty-five or thirty, seventy is an abstraction and not something that you necessarily concern yourself with. Furthermore, those who are not in the highest paid jobs do not always have the luxury of saving or spending on long term schemes such as insurance policies. There are more pressing needs to deal and the future may not be one of them. However, it is folly to ignore the inevitable and addressing just some of these issues now is better than ignoring them completely. The internet can often shed light on schemes and payment plans that you may not know about. In fact, it is an area of some considerable growth. There are also a wealth of charities and trusts that can help you if you find yourself in a difficult position. Therefore, once again I would urge readers to look to their future and not to be caught out at a time when you least need additional problems and concerns.

Last December, my 91 year old Mother suffered a rapid mental decline and was hospitalised. We have subsequently learned that this is potentially due to another stroke. Whatever the exact medical reasons, my Mother has been left bed bound, unable to feed herself and in a state of mental confusion and distress. When she was discharged home in mid January it quickly became clear that the four care visits that were scheduled each day were not sufficient for her needs, despite the staff doing their best and my Sister and I providing additional support. Matters were further compounded by personal ill health and other external factors. My Sister has worked from home for the last two years but has now started a staged return to the office. As we felt would no longer be able to cope we turned to both Social Services and the local Mental health Team for any assistance that they could provide.

In this latest post I wish to discuss hospital admissions and how they can become a regular occurrence when caring for the elderly. Being immobile, losing agency with respect to one’s personal hygiene and being dependent on medical equipment can lead to health related problems, irrespective of good home care. For example, my late Father had limited mobility and spent most of his day sitting. Hence, he used a memory foam cushion to protest against pressure sores. He also slept in a hospital bed equipped with an air mattress for similar reasons. Despite having attentive carers twice a day, he was subject to regular skin complaints due to his diet (he was fed via a PEG tube) and lack of sunlight. Perhaps the biggest source of problems came from being catheterised. Despite scrupulous cleanliness he would still regularly contract urinary tract infections. As a result hospital admissions were frequent.
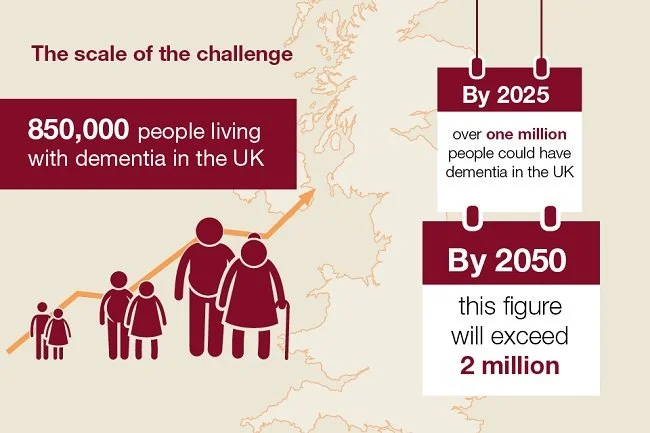
It has been over a year since I’ve written about this subject. The last post was about my late Father’s funeral. Since then life has gone on and my Mother’s ongoing care has become a fixed and somewhat uneventful regime. There are benefits to be gained from such a routine as it offers stability and certainty for both the carer and person being cared for. However, recently there has been a significant change in the status quo that warrants writing about. As always, my desire is to share some points and present my personal experiences in the hope that they may prove useful and informative to those in a similar situation or who may be just embarking upon their caring journey. The main subject of this post is a difficult one and something that is very hard to come to terms with. It is dementia. A medical condition that affects 1 in 6 people over the age of 80 in the UK.

Yesterday, Saturday 17th July, was my late Father’s birthday. He would have been 92. As my granddaughters were staying over the day was upbeat, boisterous and fun due to their exuberance. Today as the bungalow returns to its normal levels of noise and excitement, I have spent some time quietly reflecting upon the nature of bereavement. When my father died last September I was focused upon the practicalities of arranging a funeral during a pandemic, ensuring that his estate was processed and that all possible provisions were made for my disabled 90 year old Mother. These things have now been done and it is only recently that I have had the time to process my own grief. The first Father’s Day (20th June in the UK) without him was naturally a milestone and his birthday has proven similarly so. However, today’s introspection has been beneficial and hence I felt the desire to write about him and share some thoughts on the nature of bereavement.

The funeral service for my late Father was held today. As ever I would like to collate my thoughts and present them here in the hope that I may be able to assist someone else who is currently dealing with a bereavement. Funerals can be challenging at any time but are further complicated at the moment due to the various restrictions imposed due to the global COVID-19 pandemic. However, there is still scope to give a loved one a fitting send off. You just have to be a little more creative about it and try to be understanding of the current regulations regarding social gatherings. Despite my concerns today’s service at our local Borough crematorium went well, if such a term is appropriate. I feel that my Father was honoured appropriately and that his family and friends were able to pay their respects and celebrate his life in a manner that he would approve of.

Long-term care can often end with a bereavement; which is a complex subject in itself. I will not be discussing grief in this post, as that is an immensely personal and subjective experience that we deal with in our own way. Instead, I would like to talk about the administrative and logistical problems that arise after someone has died and use my own recent experiences as an example. My Father died on Wednesday 16th September. He had a series of strokes in 2016 which left him disabled. Over the last four years his level of health has slowly deteriorated and his quality of life has subsequently diminished. This year saw a noticeable change not only in his well being but overall attitude. His stoical outlook finally faded and he lost all interest in life. He fell ill in mid August with Sepsis and then developed a lung infection. When I saw him last on Friday 4th September he told me he was tired and wanted “an end to it all”. Six days later he asked the Senior Doctor on the ward to stop treatment, which wasn’t working anyway. He died a week later on Wednesday 16th September. He was 91.

I last wrote a post about “caring for the elderly” in February. There have been significant changes in my family's fortunes since then and like anyone in a caring situation, the lockdown has had a major impact and sadly not for the good. As ever, I choose to recount my own experiences in the hope that they may be of some use to others who are in a similar situation. So to begin with, my Mother went into Respite Care just as the pandemic was hitting the UK and the lockdown was being implemented. Hence her stay in a nursing home was not the best experience. All the additional social activities usually on offer were suspended so all she effectively did was swap one sick room for another. She came back home just as my sister moved from working in London to working from home. Hence from March onwards both her and I have been caring for both my disabled parents on a daily basis. However, my sister has had to hold down a job at the same time.

My Mother, who has had limited mobility for a decade, fell and broke her arm just before Christmas. She subsequently spent nine weeks at a specialist rehabilitation unit at our local hospital. During that time she had surgery on her arm to repair the fracture and extensive physiotherapy to try and increase her mobility. She was discharged at the beginning of February with a support package in place to facilitate her return home. Sadly, despite physiotherapy, she is immobile as the day she was admitted. Until she sees the Consultant at the Fracture Clinic and is told if her arm can bear weight, she is not allowed to do anything for herself. Hence she is currently having four home visits a day from two carers and is confined to her bedroom. The carers help her get washed, dressed and use the commode in her room. Naturally, the current situation and the inability to do anything for herself, along with the uncertainty of her long term recovery and future, is causing a great deal of anxiety not only for my Mother but the rest of the family as well. At present we have a 3 week wait before she gets to see the consultant.

I always try to write the posts in this series in way that proves useful to others who are facing a similar experience. Caring, old age, illness and our own mortality are all matters that will cross our path sooner or later. This time I shall be addressing a subject that many of us tread carefully around. Some people will not countenance discussing it in any way, shape or form as it makes us uncomfortable or even scared. In Western culture death is often the elephant in the room; a topic that should not be avoided but frequently is, due to etiquette and other curious societal foibles. Hence, we use phrase like “passed” or “gone” instead of dead and we often invoke religious based platitudes, regardless of whether we have any particular faith or not. Simply put, our response to the inevitability of our own demise and that of those who we love is ambiguous to say the least. I hope in the years to come we grow up in this respect and find a comfortable means of making death socially acceptable to discuss and plan for.

I started writing this series of blog posts when I first became a carer back in 2016. The idea has always been to use my personal experiences as a point of reference for others. That is the main reason for this latest update. The things that are currently happening to me and my nearest and dearest may happen to you and yours. Over the last three years a lot has changed in my family’s collective life. Both my parents have gone from living relatively independently and managing their own affairs, to becoming disabled with long term degenerative medical conditions. Both are now housebound and require assistance with basic tasks such as washing and dressing, due to reduce mobility and frailty. My Father has been nil by mouth for three years and requires district nurse visits twice a day to deal with his medicine and catheter. My Sister has altered her working hours so she has more time available in the morning before she goes to work. I have given up work to become a fulltime carer. Between us the days is covered. The latest major change has been applying for power of attorney, which I wrote about in my previous post.

Since spring 2016, I have been running my parent’s domestic affairs. Due increasing ill health, neither can visit a bank, conduct business phone calls or deal with administrative paperwork such as utility bills, insurance policies and hospital appointments. However, there are limits on what I can and cannot do. Cheques and legal documents need signatures. UK data protection legislation often prohibits phone conversations with anyone other than the account holder. Hence despite being able to broadly deal with most things that come up, I sometimes have to involve my parents. This mean conversations on speaker phones which are difficult when both my parents have substantial hearing loss. So after some discussion with both of my parents, I have decided to pursue the power of attorney. At present this is specifically for my Father, as most bills and invoices are in his name.

Once again, I find myself writing about this subject in the hope that it will encourage others to reflect upon the nature of old age, illness and the consequences that arise from them. There is still a prevailing culture of not discussing and sometimes not even thinking about such matters, but both are an absolute certainty in everyone’s life. All too often people find themselves in extremely difficult situations brought about by such events and the difficulty and emotional trauma is increased due to there being no plan in place or provision to address matters. Therefore, I strongly advocate the following. Some may seem like very obvious points, but recent conversations I’ve had with other carers and people in similar situations, has shown that many people have not made even the most basic of provisions in this regard.

At the end of July, my Father went into Respite Care for two weeks. He was placed in a local private nursing home, via borough social services. The placement was intended to provide him a change of scenery and give the rest of the family with a short break from the ongoing caring requirements. Sadly, things did not work out well. After seven days away from home, my Father became ill and after three trips to A&E (over a period of four days), he was finally admitted to hospital with Aspiration Pneumonia. He was deemed to be at extreme risk by the medical staff and we were told at one point to “prepare for the worse”. However, despite being seriously ill, he recovered and much to everyone’s surprise was discharged and returned home after ten days. Sadly, his already impaired state of health has been further diminished. Three weeks on it is becoming clear that it is unlikely that he will return to the level of ability that he had at the start of July. His health and the quality of his life has been further reduced. Subsequently, the various healthcare professionals that deal with my Father have now started using the term palliative care.

There comes a stage in most people’s life when they start reflecting upon their own mortality. Both my parents have survived two strokes each and are now in the late eighties. At this point in their lives healthcare has moved on from correcting or remedying problems, to instead being more about holding the line and maintaining the status quo. A safe home along with an orderly daily routine provides a stable environment, which broadly allows them both to maintain an adequate degree of independent living. However, both are very aware that their faculties and overall health are gradually diminishing. Neither are naïve or foolish enough to deny this and in recent months have been quite candid about what the future will entail. Simply put both my parents are aware that they are currently “running the last lap”, to use one of their phrases.

I have written in the past about caring for the elderly. I have approached the subject from a personal perspective, as a carer with two disabled octogenarian parents, as well as considering the broader needs of a society with an ageing population. As it has been two years since I formally became a carer to both my parents, I thought I’d share my experiences on the many challenges that my family has faced over the last twenty-four months. I find doing so beneficial and maybe my anecdotes may be of value to others in a similar situation. As I’ve said in my original post, caring for a loved one is something we all potentially face at some point in our lives, and with an ageing population it becomes statistically more likely each year.

In a previous post, written last summer, I mentioned my caring commitments and reflected upon the realities of being a carer. Since then my family’s circumstances have changed considerably and subsequently so have my own. In the UK, social care has become a major political issue and was a key area of debate for all parties in the recent election campaign. Although the UK has an aging population, then NHS broadly manages to deal with its needs. It is the social care that so often follows time spent in hospital, that causes a bottleneck. Too often, the local authorities struggle to find carers and have them in place when requested. This means that many patients are unable to be discharged and have to remain in hospital. Caring is a profession that seems to be greatly lauded and esteemed by politicians in principle but the reality is far different. Overall it is often a poorly paid job, with little or no employments rights or benefits.

The UK population grew by half a million last year to 65.1 million, according to figures from the Office for National Statistics. Of that number 10% are over 75 years old. At present there are 6.5 million carers in the UK, many of whom are coping with an aging parent(s). As healthcare in the UK improves overall life expectancy, the population is rapidly aging which means that every year over 2.1 million adults become carers (although almost as many people find that their caring responsibilities come to an end). This turnover means that most families in the UK face this issue at some time and 3 in 5 people will become carers during their lives.
 Roger Edwards
My Mother moved into a care home on April 7th this year. Her health was already very poor due to her age (91). She was bed bound, partially sighted, suffering from increasing hearing loss and unable to feed herself. Rapid onset dementia meant that her behaviour had become erratic and she was a danger to herself. Hence her caring needs could no longer be safely managed within a home environment. Fortunately the care home proved a good choice. For the past four months they have provided outstanding care and have treated my Mother with dignity, respect and genuine kindness. Sadly, during that time my Mother had several bouts of illness that saw her hospitalised four times. Eventually a PEACE plan (Proactive Elderly Advanced Care) was set up allowing treatment to be managed by the care home and local GP. Since July my Mother has enjoyed a stable environment and continuity of care.